
Verospiron
Cheaper & Alternative Brands
Same generic (Spironolactone), same form (Tablet)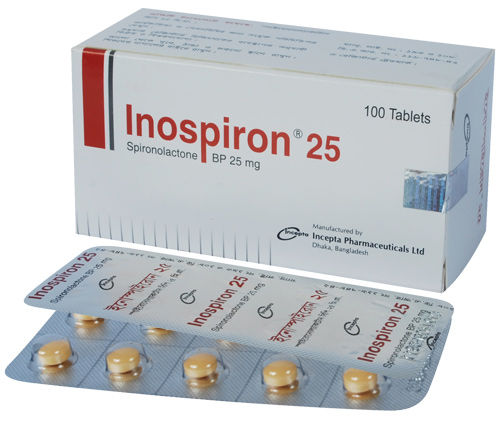

Clinical Prescribing Information
Medical monograph and safety information for healthcare professionals & patients.Indications & Clinical Uses
Inospiron is indicated for the management of edema and ascites in cirrhosis of the liver, malignant ascites, nephrotic syndrome, congestive heart failure and primary hyperaldosteronism.
Dosage & Administration
Heart Failure
: Initiate treatment at 25 mg once daily
Hypertension
: Initiate treatment at 25 to 100 mg daily in either single or divided doses
Essential hypertension
: For adults, an initial daily dosage of 50 to 100 mg of Spironolactone administered in either single or divided doses is recommended.
Primary hyperaldosteronism
: Spironolactone may be employed as an initial diagnostic measure to provide presumptive evidence of primary hyperaldosteronism while patients are on normal diets.
Edema in adults
(congestive heart failure, hepatic cirrhosis, or nephrotic syndrome): An initial daily dosage of 50-100 mg of Spironolactone administered in either single or divided doses is recommended, but may range from 25 to 200 mg daily.
Hypokalemia
: Spironolactone in a dosage ranging from 25 mg to 100 mg daily is useful in treating a diuretic-induced hypokalemia, when oral potassium supplements or other potassium-sparing regimens are considered inappropriate.
Contraindications
Acute renal insufficiency, significant impairment of renal function, anuria, hyperkalemia or sensitivity to Spironolactone.
Side Effects & Adverse Reactions
Gynaecomastia may develop in association with the use of Inospiron. The development of gynaecomastia appears to be related to both dosage level & duration of therapy and is normally reversible when Inospiron is discontinued. In rare instances, some breast enlargement may persist.
Other adverse reactions that have been reported in association with Inospiron are: gastrointestinal symptoms including cramping and diarrhoea, drowsiness, lethargy, headache, maculopapular or erythematous cutaneous eruptions, urticaria, mental confusion, drug fever, ataxia, impotence, irregular menses or amenorrhoea, and post-menopausal bleeding. Adverse reactions are usually reversible upon discontinuation of the drug.
Warnings & Precautions
All patients receiving diuretic therapy should be observed for evidence of fluid or electrolyte imbalance, eg, hypomagnesemia, hyponatremia, hypochloremic alkalosis, and hyperkalemia. Serum and urine electrolyte determinations are particularly important when the patient is vomiting excessively or receiving parenteral fluids. Hyperkalemia may occur in patients with impaired renal function or excessive potassium intake and can cause cardiac irregularities, which may be fatal. Consequently, no potassium supplement should ordinarily be given.
Pharmacology & Mechanism of Action
Description
: Spironolactone is an antagonist of aldosterone & potassium-sparing diuretic. It acts primarily through competitive binding of receptors at the aldosterone dependent sodium-potassium exchange site in the distal convoluted renal tubule. Spironolactone causes increased amounts of sodium and water to be excreted, while potassium and magnesium is retained.
Mode of action
: Spironolactone and its active metabolites are specific pharmacologic antagonists of aldosterone, acting primarily through competitive binding of receptors at the aldosterone-dependent sodium-potassium exchange site in the distal convoluted renal tubule. Spironolactone causes increased amounts of sodium and water to be excreted, while potassium is retained. Spironolactone acts both as a diuretic and as an antihypertensive drug by this mechanism. It may be given alone or with other diuretic agents that act more proximally in the renal tubule.
Absorption
: The mean time to reach peak plasma concentration of spironolactone and the active metabolite, canrenone, in healthy volunteers is 2.6 and 4.3 hours, respectively. Effect of food: Food increased the bioavailability of spironolactone (as measured by AUC) by approximately 95.4%. Patients should establish a routine pattern for taking Spironolactone with regard to meals.
Distribution
: Spironolactone and its metabolites are more than 90% bound to plasma proteins.
Metabolism
: Spironolactone is rapidly and extensively metabolized. Metabolites can be divided into two main categories: those in which sulfur of the parent molecule is removed (e.g., canrenone) and those in which the sulfur is retained (e.g., TMS and HTMS).In humans, the potencies of TMS and 7-a-thiospirolactone in reversing the effects of the synthetic mineralocorticoid, fludrocortisone, on urinary electrolyte composition were approximately a third relative to spironolactone.
Elimination & Excretion
: The mean half-life of spironolactone is 1.4 hour.The mean half-life values of its metabolites including canrenone, 7-a-(thiomethyl) spirolactone (TMS), and 6-B-hydroxy-7-a-(thiomethyl) spirolactone (HTMS) are 16.5, 13.8, and 15 hours, respectively. The metabolites are excreted primarily in the urine and secondarily in bile.