
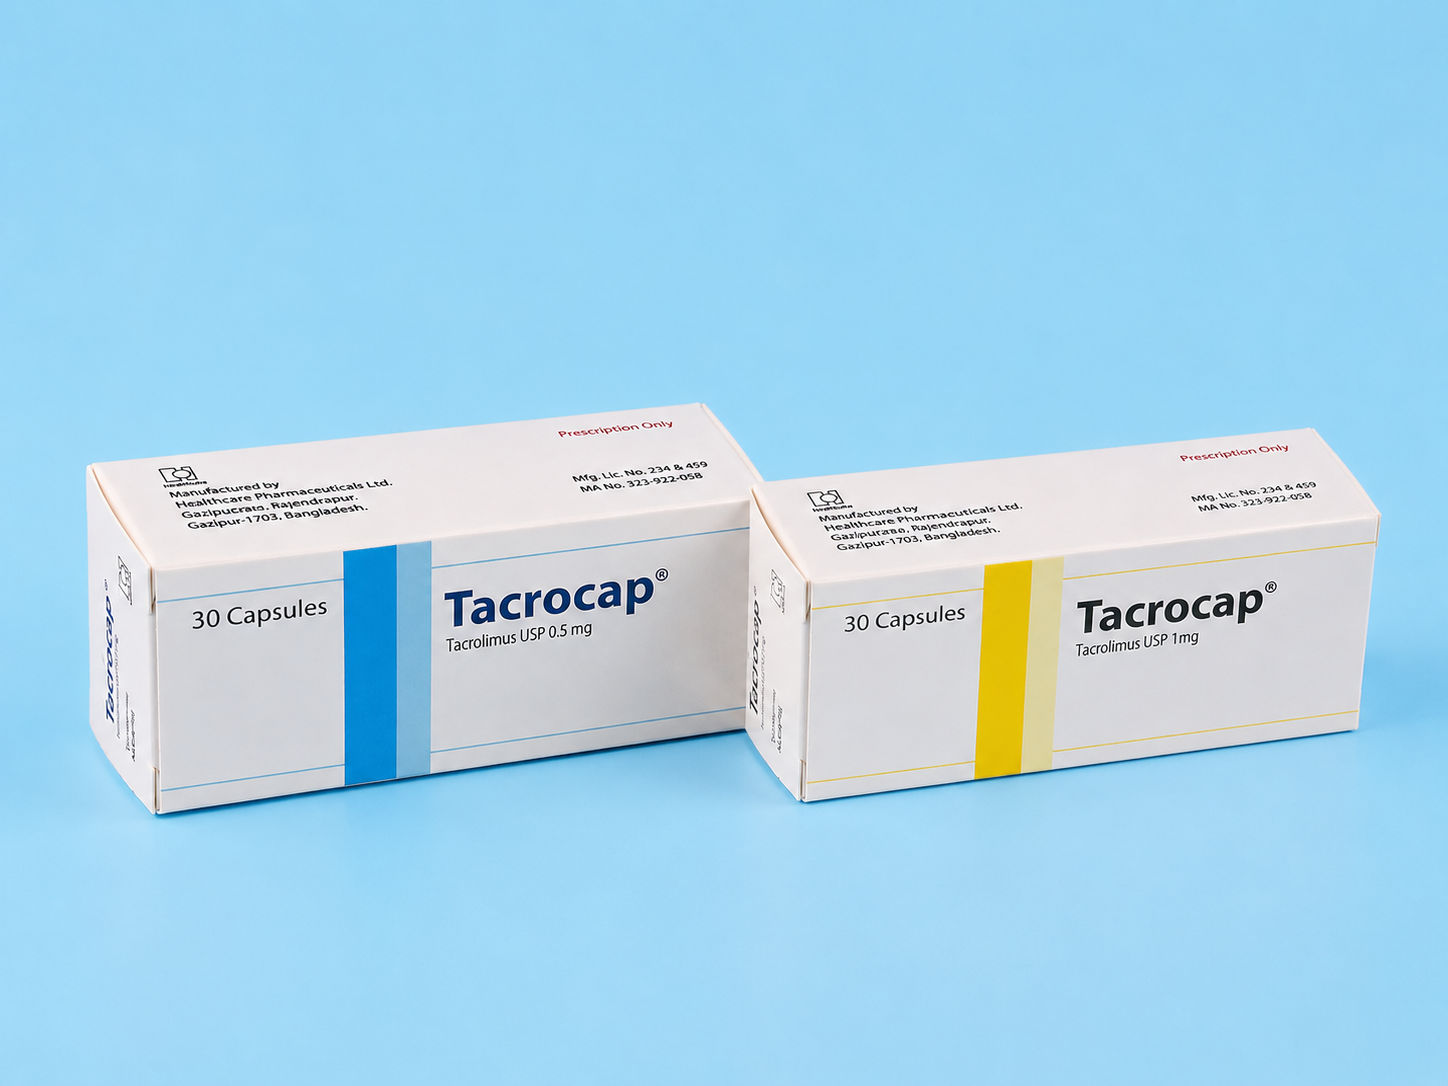
Tacromus
Cheaper & Alternative Brands
Same generic (Tacrolimus Monohydrate), same form (Capsule)

Clinical Prescribing Information
Medical monograph and safety information for healthcare professionals & patients.Indications & Clinical Uses
Crilomus is a calcineurin-inhibitor immunosuppressant indicated for the prophylaxis of organ rejection in adult and pediatric patients receiving allogeneic liver, kidney, heart, or lung transplants, in combination with other immunosuppressants.
Dosage & Administration
If patients are able to tolerate oral therapy, the recommended oral starting doses should be initiated.
The initial dose of Tacrolimus capsules should be administered no sooner than 6 hours after transplantation in the liver, heart, or lung transplant patients.
In kidney transplant patients, the initial dose of Tacrolimus capsules may be administered within 24 hours of transplantation but should be delayed until renal function has recovered.
Initial Oral Tacrolimus Capsules Dosage Recommendations and Whole Blood Trough Concentration Range in Adults
:
Adult Patients
Initial oral dosage of Tacrolimus. Daily doses should be administered every 12 hours
Whole blood trough concentration range
Kidney transplant patients:
In combination with azathioprine
In combination with MMF/IL-2 receptor antagonist
0.2 mg/kg/day
0.1 mg/kg/day
month 1-3: 7-20 ng/mL
month 4-12: 5-15 ng/mL
month 1-12: 4-11 ng/mL
Liver transplant patients:
With corticosteroids only
0.10-0.15 mg/kg/day
month 1-12: 5-20 ng/mL
Heart transplant patients:
With azathioprine or MMF
0.075 mg/kg/day
month 1-3: 10-20 ng/mL
month ≥4: 5-15 ng/mL
Lung Transplant patients:
With azathioprine or MMF
0.075 mg/kg/day
Month 1-3: 10-15 ng/mL
Month 4-12: 8-12 ng/mL
Note
: In lung transplantation, cystic fibrosis patients may have a reduced bioavailability of orally administered tacrolimus resulting in the need for higher doses to achieve target tacrolimus trough concentrations. Monitor tacrolimus trough concentrations and adjust the dose accordingly.
Initial Oral Tacrolimus Capsules Dosage Recommendations and Whole Blood Trough Concentration Range in Childrens
:
Pediatric Patients
Initial oral dosage of Tacrolimus. Daily doses should be administered every 12 hours.
Whole blood trough concentration range
Kidney transplant patients
0.3 mg/kg/day
Month 1-12: 5-20 ng/mL
Liver transplant patients
0.15-0.2 mg/kg/day
Month 1-12: 5-20 ng/mL
Heart transplant patients
0.3 mg/kg/day
Month 1-12: 5-20 ng/mL
Lung transplant patients
0.3 mg/kg/day
Week 1-2: 10-20 ng/mL
Week 2 to Month 12: 10-15 ng/mL
Note
: In lung transplantation, cystic fibrosis patients may have a reduced bioavailability of orally administered tacrolimus resulting in the need for higher doses to achieve target tacrolimus trough concentrations. Monitor tacrolimus trough concentrations and adjust the dose accordingly.
Contraindications
Hypersensitivity to tacrolimus or HCO-60 (polyoxyl 60 hydrogenated castor oil).
Side Effects & Adverse Reactions
The most common adverse reactions (≥15%) were abnormal renal function, hypertension, diabetes mellitus, fever, CMV infection, tremor, hyperglycemia, leukopenia, infection, anemia, bronchitis, pericardial effusion, urinary tract infection, constipation, diarrhea, headache, abdominal pain, insomnia, paresthesia, peripheral edema, nausea, hyperkalemia, hypomag-nesemia, and hyperlipemia.
Warnings & Precautions
Not Interchangeable with Extended-Release Crilomus Products- Medication Errors
: Instruct patients or caregivers to recognize the appearance of Crilomus capsules.
New Onset Diabetes After Transplant
: Monitor blood glucose.
Nephrotoxicity (acute and/or chronic)
: Reduce the dose; use caution with other nephrotoxic drugs.
Neurotoxicity
: Including risk of Posterior Reversible Encephalopathy Syndrome (PRES); monitor for neurologic abnormalities; reduce or discontinue Crilomus.
Hyperkalemia
: Monitor serum potassium levels. Consider carefully before using with other agents also associated with hyperkalemia.
Hypertension
: May require antihypertensive therapy. Monitor relevant drug-drug interactions.
Anaphylactic Reactions with IV formulation
: Observe patients receiving Crilomus injection for signs and symptoms of anaphylaxis.
Not recommended for use with sirolimus
: Not recommended in liver and heart transplant due to increased risk of serious adverse reactions.
Myocardial Hypertrophy
: Consider dose reduction/discontinuation.
Immunizations
: Avoid live vaccines.
Pure Red Cell Aplasia
: Consider discontinuation of Crilomus.
Thrombotic Microangiopathy, Including Hemolytic Uremic Syndrome and Thrombotic
Thrombocytopenic Purpura
: May occur, especially in patients with infections and certain concomitant medications.
Pharmacology & Mechanism of Action
Tacrolimus binds to an intracellular protein, FKBP-12. A complex of tacrolimus-FKBP-12, calcium, calmodulin, and calcineurin (a ubiquitous mammalian intracellular enzyme) is then formed, after which the phosphatase activity of calcineurin is inhibited. Such inhibition preventsthe dephosphorylation and translocation of various factors such as the nuclear factor of activated T-cells (NF-AT), and nuclear factor kappa-light-chain enhancer of activated B-cells (NF-κB).
Tacrolimus inhibits the expression and/or production of several cytokines that include interleukin (IL)-1 beta, IL-2, IL-3, IL-4, IL-5, IL-6, IL-8, IL-10, gamma interferon, tumor necrosis factor-alpha, and granulocyte macrophage colony-stimulating factor. Tacrolimus also inhibits IL-2 receptor expression and nitric oxide release, induces apoptosis and production of transforming growth factor beta that can lead to immunosuppressive activity. The net result is the inhibition of T-lymphocyte activation and proliferation, as well as T-helper-cell-dependent B-cell response (i.e., immunosuppression).