
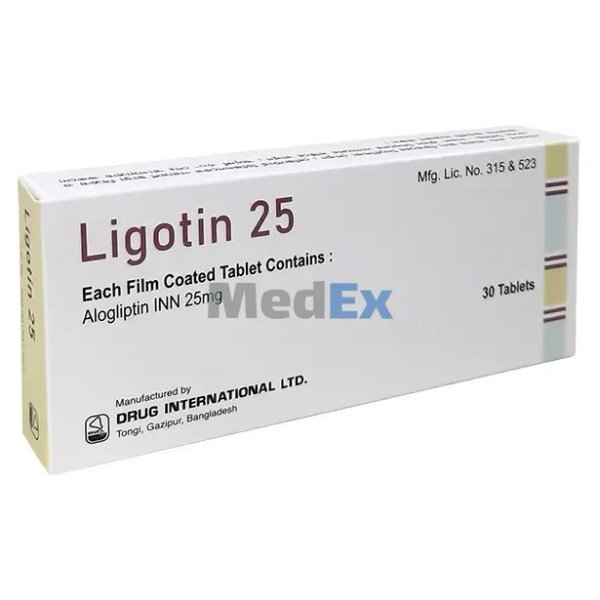
Ligotin
 Generic: Alogliptin Benzoate
 Daily Dose:
 Duration:
 Alternatives (8)
Cheaper & Alternative Brands
Same generic (Alogliptin Benzoate), same form (Tablet)



Clinical Prescribing Information
Medical monograph and safety information for healthcare professionals & patients.Indications & Clinical Uses
Aglip is indicated as an adjunct to diet and exercise to improve glycaemic control in adults with type-2 diabetes mellitus.
Dosage & Administration
The recommended dose in patients with normal renal function or mild renal impairment is 25 mg once daily or as directed by the physicians.
Contraindications
History of a serious hypersensitivity reaction to Alogliptin-containing products, such as anaphylaxis, angioedema or severe cutaneous adverse reactions.
Side Effects & Adverse Reactions
Common side effects are nasopharyngitis, headache and upper respiratory tract infection.
Warnings & Precautions
Acute pancreatitis
: If pancreatitis is suspected, promptly Aglip should be discontinued.
Hypersensitivity
: There have been postmarketing reports of serious hypersensitivity reactions in patients treated with Aglip such as anaphylaxis, angioedema and severe cutaneous adverse reactions. In such cases, promptly Aglip should be discontinued.
Hepatic effects
: Postmarketing reports of hepatic failure, sometimes fatal. Causality can not be excluded. If liver injury is detected, promptly interrupt Aglip and assess patient for probable cause, then treat cause if possible, to resolution or stabilization. Do not restart Aglip if liver injury is confirmed and no alternative etiology can be found.
Hypoglycemia
: When an insulin secretagogue (e.g. sulfonylurea) or insulin is used in combination with Aglip, a lower dose of the insulin secretagogue or insulin may be required to minimize the risk of hypoglycaemia.
Macrovascular outcomes
: There have been no clinical studies establishing conclusive evidence of macrovascular risk reduction with Aglip or any other antidiabetic drug.
Pharmacology & Mechanism of Action
Alogliptin is a DPP-4 inhibitor that slows the inactivation of the incretin hormones, thereby increasing their bloodstream concentrations and reducing fasting and postprandial glucose concentrations in a glucose-dependent manner in patients with type 2 diabetes mellitus. Increased concentrations of the incretin hormones such as glucagon-like peptide-1 (GLP-1) and glucose-dependent insulinotropic polypeptide (GIP) are released into the bloodstream from the small intestine in response to meals. These hormones cause insulin release from the pancreatic beta cells in a glucose-dependent manner but are inactivated by the DPP-4 enzyme within minutes. GLP-1 also lowers glucagon secretion from pancreatic alpha cells, reducing hepatic glucose production. In patients with type 2 diabetes, concentrations of GLP-1 are reduced but the insulin response to GLP-1 is preserved.