
Dermova
Cheaper & Alternative Brands
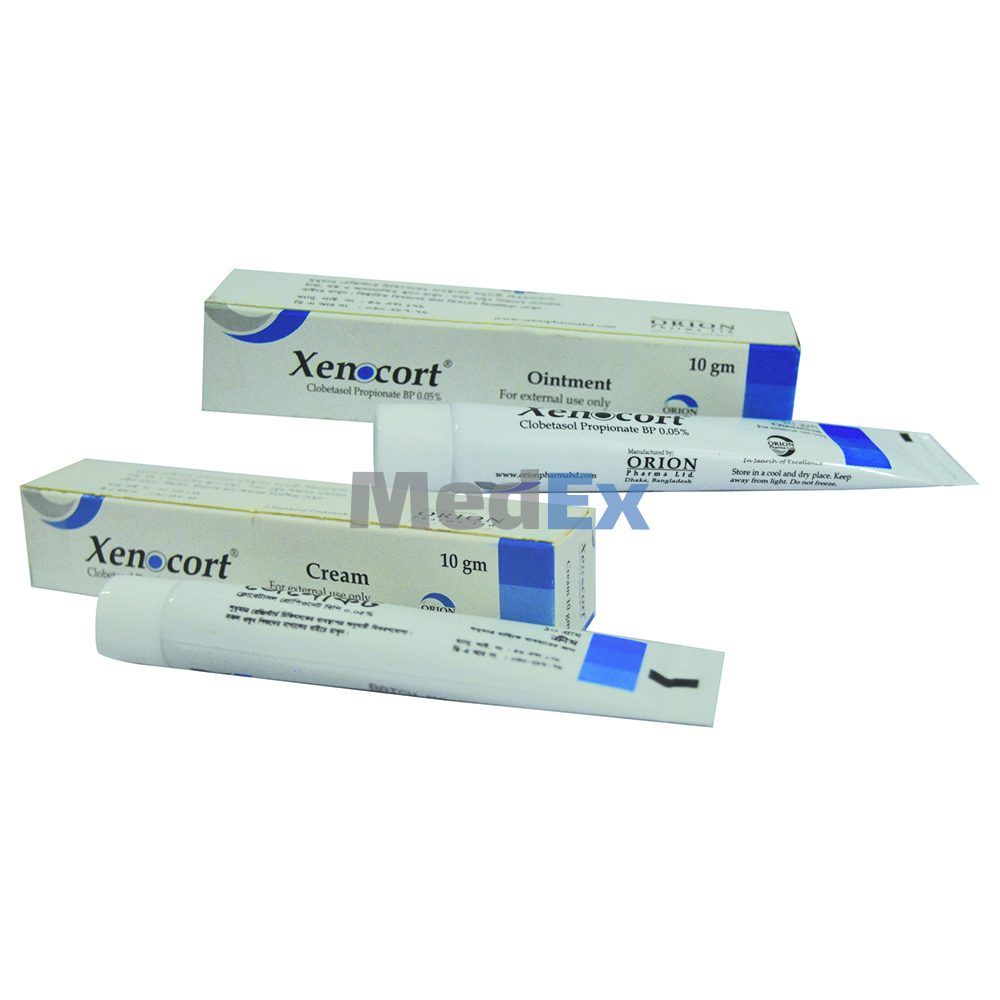
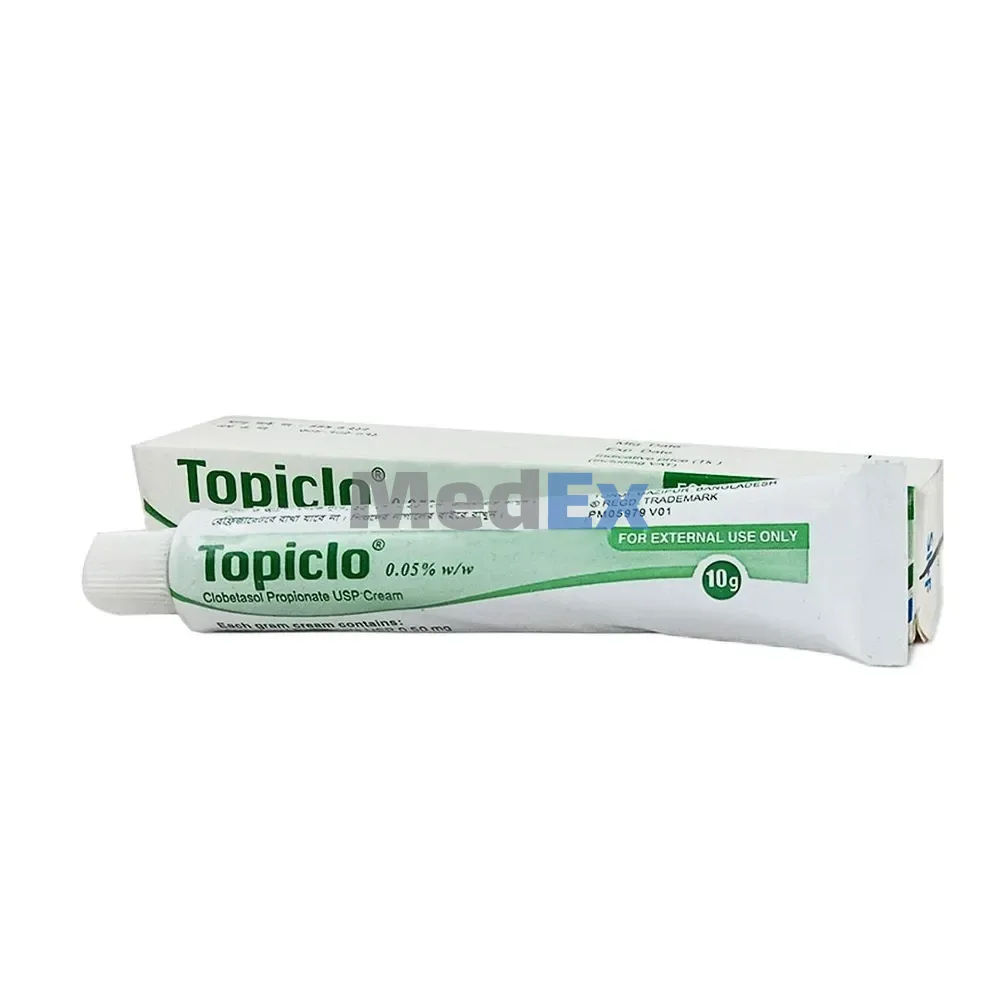
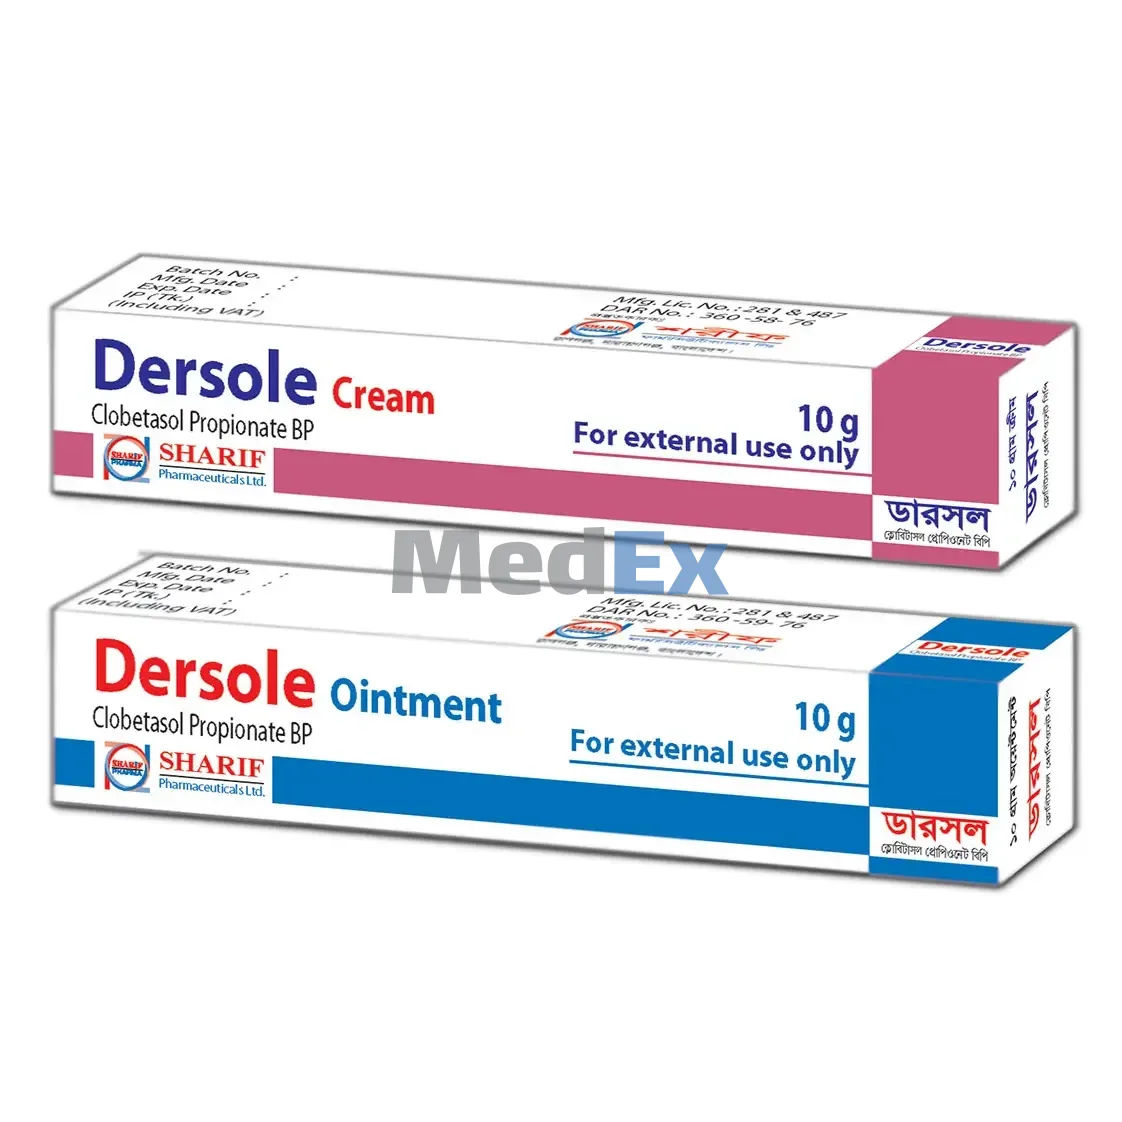
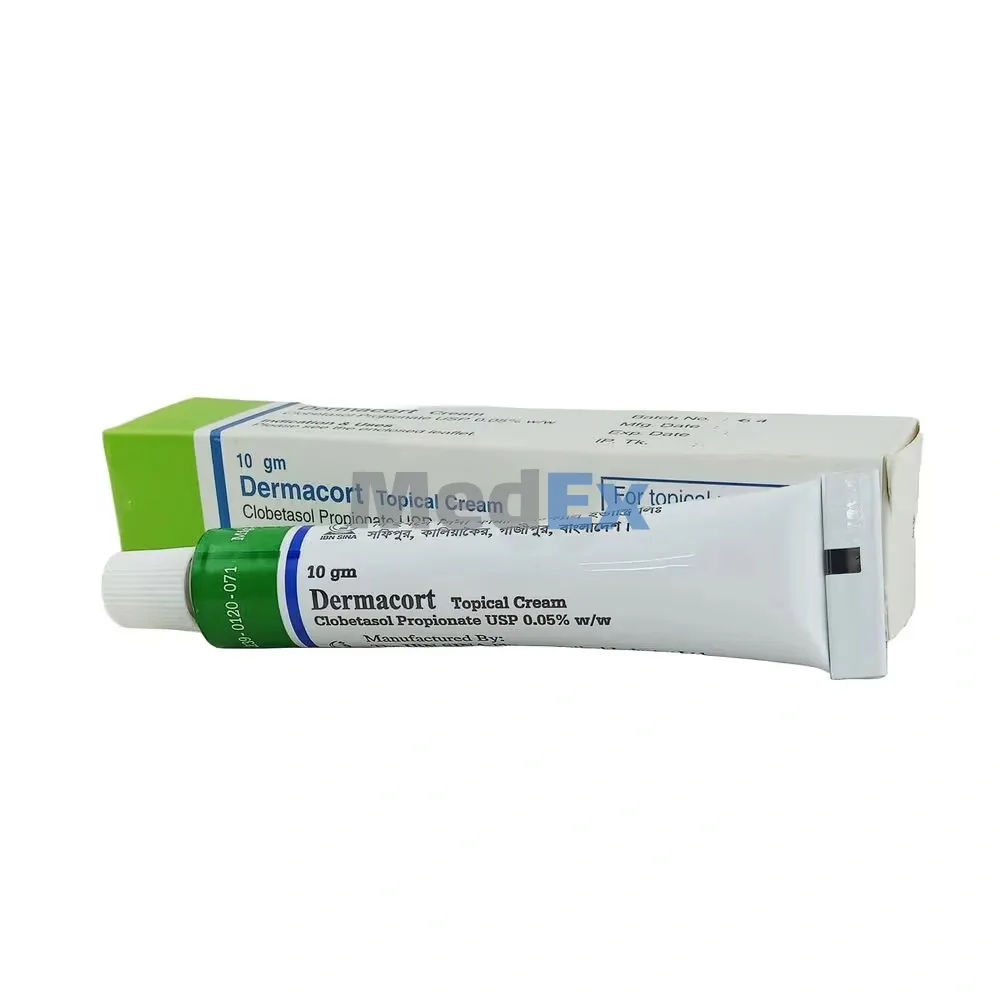
Same generic (Clobetasol Propionate), same form (Cream)


Clinical Prescribing Information
Medical monograph and safety information for healthcare professionals & patients.Indications & Clinical Uses
Aclobet is indicated for adults, elderly and children over 1 year in following dermatoses.
Psoriasis (excluding widespread plaque psoriasis)
Recalcitrant dermatoses
Lichen planus
Discoid lupus erythematosus
Other skin conditions which do not respond satisfactorily to less potent steroids.
Contraindications
Rosacea, acne vulgaris and perioral dermatitis. Primary cutaneous viral infections (e.g. herpes simplex, chickenpox).
Hypersensitivity to the preparation.
The use of Clobetasol Propionate skin preparations is not indicated in the treatment of primarily infected skin lesions caused by infection with fungi (e.g. candidiasis, tinea), or bacteria (e.g.impetigo): perianal and genital pruritus.
Dermatoses in children under one year of age, including dermatitis and napkin eruptions.
Side Effects & Adverse Reactions
As with other topical corticosteroids prolonged use of large amounts, or treatment of extensive areas can result in sufficient systemic absorption to produce the features of hypercorticism.
Prolonged and intensive treatment with a highly active corticosteroid preparation may cause local atrophic changes in the skin such as thinning, striae and dilatation of the superficial blood vessels, particularly when occlusive dressings are used or when skin folds are involved.
In rare instances, treatment of psoriasis with corticosteroids (or its withdrawal) is thought to have provoked the pustular form of the disease.
There are reports of pigmentation changes and hypertrichosis with topical steroids. Aclobet is usually well tolerated, but if signs of hypersensitivity appear, application should be stopped immediately. Exacerbation of symptoms may occur.
Warnings & Precautions
Long-term continuous topical therapy should be avoided where possible, particularly in infants and children, as adrenal suppression can occur readily even without occlusion. If used in childhood or on the face, courses should be limited if possible to five days and occlusion should not be used.
The face, more than other areas of the body, may exhibit atrophic changes after prolonged treatment with potent topical corticosteroids. This must be borne in mind when treating such conditions as psoriasis, discoid lupus erythematosus and severe eczema.
If applied to the eye lids, care is needed to ensure that the preparation does not enter the eye, as glaucoma or cataract might result.
Topical corticosteroids may be hazardous in psoriasis for a number of reasons including rebound relapses, development of tolerance, risk of generalised pustular psoriasis and development of local or systemic toxicity due to impaired barrier function of the skin. If used in psoriasis careful patient supervision is important.
Appropriate anti-microbial therapy should be used whenever treating inflammatory lesions which have become infected. Any spread of infection requires withdrawal of topical corticosteroid therapy and systemic administration of anti-microbial agents. Bacterial infection is encouraged by the warm, moist conditions induced by occlusive dressings, and so the skin should be cleansed before a fresh dressing is applied.
Pharmacology & Mechanism of Action
Clobetasol Propionate is a very potent topical corticosteroid. It has anti-inflammatory, antipruritic and vasoconstrictive properties. It shows anti-inflammatory activity via multiple mechanisms to inhibit late phase allergic reactions. It decreases the density of mast cells, chemotaxis and activation of eosinophils. It also reduces cytokine production and inhibits the metabolism of arachidonic acid.
Like other topical corticosteroids, clobetasol propionate has anti-inflammatory, antipruritic and vasoconstrictive properties. The mechanism of the anti-inflammatory activity of the topical steroids, in general, is unclear. However, corticosteroids are thought to act by induction of phospholipase A2 inhibitory proteins, collectively called lipocortins. It is postulated that these proteins control the biosynthesis of potent mediators of inflammation such as prostaglandins and leukotrienes by inhibiting the release of their common precursor, arachidonic acid. Arachidonic acid is released from membrane phospholipids by phospholipase A2.